
 Jain Pain Clinic
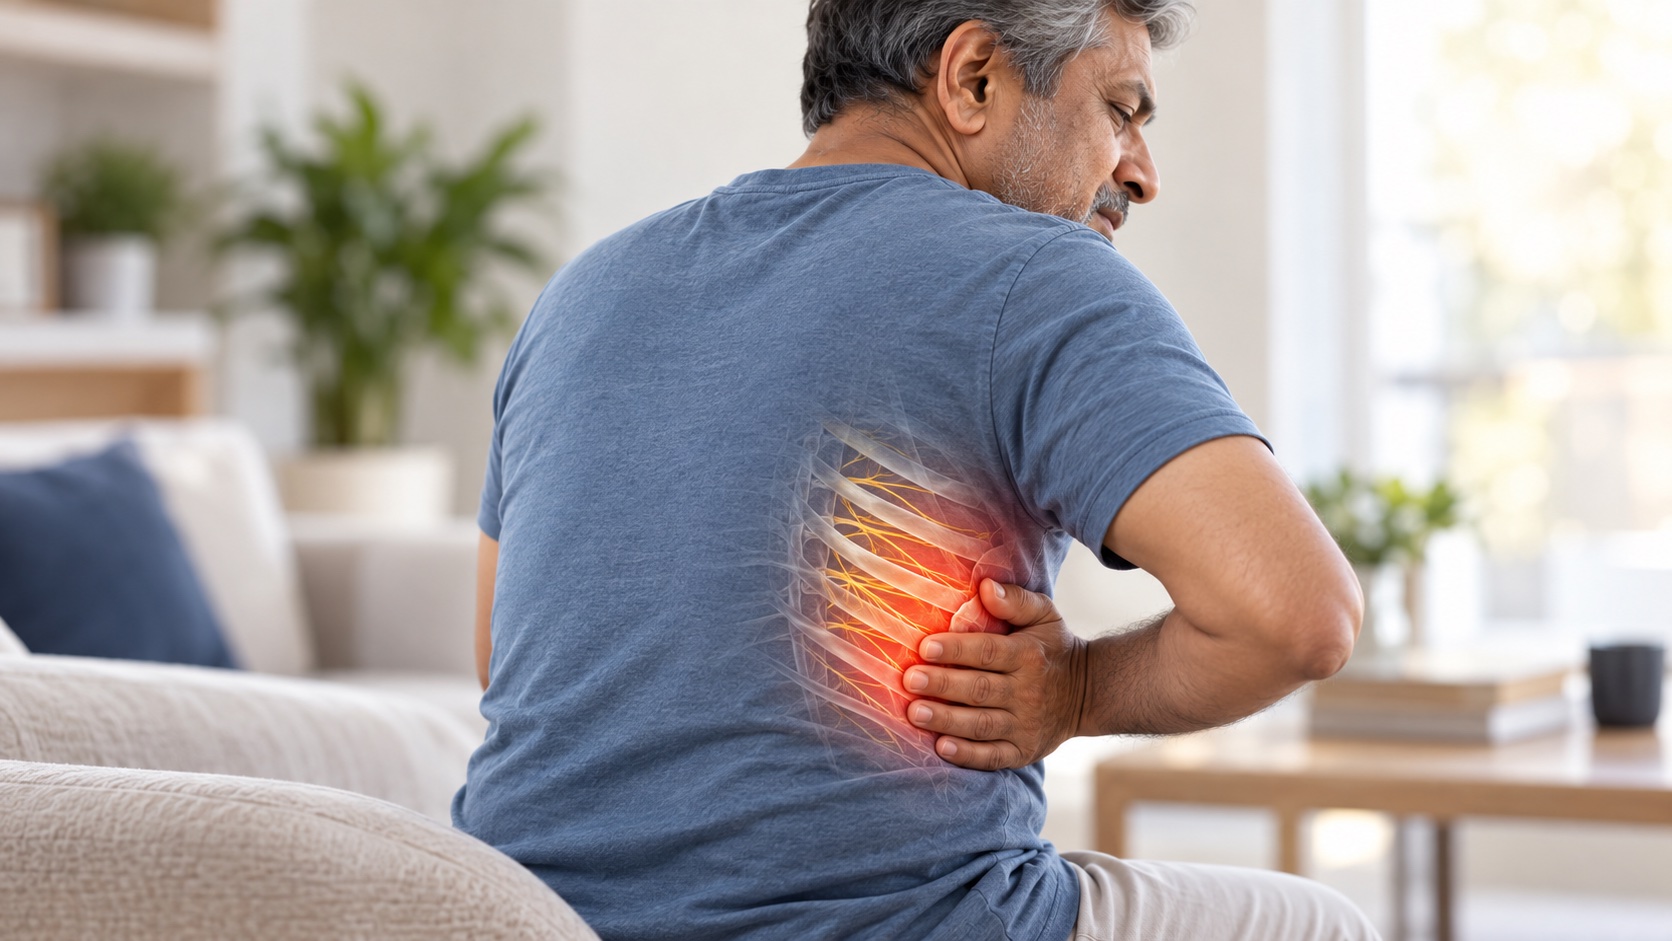
The shingles rash has faded, but a shirt brushing the skin still hurts. Sleep is broken by burning pain, and the area may feel both numb and sensitive. This can happen when nerves remain affected after shingles. Persistent pain is often called postherpetic neuralgia. It deserves assessment and a plan that considers comfort, sleep and daily activity, rather than simply waiting for the skin to look normal.
On this page
Why Can Pain Continue After the Rash?
Shingles occurs when the virus that causes chickenpox becomes active again. It affects nerves and the skin supplied by them. Even after the rash heals, injured nerves may continue producing abnormal pain signals. Visible skin recovery and nerve recovery do not necessarily happen together.
Postherpetic neuralgia commonly refers to pain persisting for three months or more after the rash began. You do not need to wait for that point to ask for help. Pain that is difficult to manage during the rash or in the following weeks also needs attention.
What Does Postherpetic Neuralgia Feel Like?
The pain usually affects the area where the shingles rash occurred. It may be burning, aching or sharp, and can be continuous or come in bursts. Light touch, clothing or a bedsheet can become painful; this response to normally harmless contact is called allodynia. Itching or reduced sensation may occur too.
A useful description separates the background ache from sudden pain episodes and touch sensitivity. Tell your clinician which part most affects you. For example, being unable to tolerate a waistband is a different everyday problem from waking repeatedly with stabbing pain.
Is This Lingering Pain or a New Shingles Episode?
A new blistering rash needs prompt medical advice. Antiviral treatment for a fresh episode works best when started early, usually within 72 hours of rash onset. If that window has passed, still seek advice; the decision depends on your symptoms and health.
Get urgent assessment for a rash on the eye or nose, vision changes or symptoms in someone with a severely weakened immune system. Pain in a previously affected area should not be assumed to explain a new or different illness. New chest pain, for example, needs assessment on its own merits.
How Is Persistent Pain Assessed?
The history of shingles, the location of the rash and an examination often establish the diagnosis. Tests are not routinely needed for every typical case, but unusual symptoms may require further investigation. Older age and a severe initial episode increase the risk of persistent pain.
Bring the date the rash started, photographs if you already have them, and details of treatment received. Record whether the skin has fully healed and whether symptoms are improving, stable or worsening. This helps distinguish ongoing recovery from a problem needing a different assessment.
Why Might Ordinary Painkillers Be Insufficient?
Nerve pain may need a different treatment approach from an everyday muscle ache. Clinicians may consider medicines such as amitriptyline, duloxetine, gabapentin or pregabalin, depending on suitability. Some medicines used for depression or seizures also help nerve pain; their use does not mean that pain is imagined or that you have those conditions.
Treatment is often started cautiously and reviewed over time. Benefits may take time to judge, while sleepiness, dizziness or other side effects can limit treatment. Kidney function, other medicines and the risk of falls can affect the choice. Do not change doses or stop a prescribed medicine without discussing the plan.
Ask what improvement would count as worthwhile and when the next review should happen. A treatment that makes you too sleepy to function needs review even if the pain score has fallen.
Can Creams, Patches or Procedures Help?
Local treatments may be considered for a defined painful area. Lidocaine patches can be useful for selected patients. Capsaicin products are another option, but stronger patches need professional application and monitoring. These approaches have different instructions; do not treat them as interchangeable or apply them to open or unhealed skin.
If pain remains severe, a specialist may discuss additional options, including selected procedures. Ask what benefit is expected, how strong the evidence is and what the risks are. No single intervention reliably removes postherpetic neuralgia for everyone, and a procedure should have a specific purpose in the wider plan.
Making Everyday Life More Comfortable
Loose, soft clothing may reduce irritation. A wrapped cool compress may help some people; avoid putting ice directly on the skin. Do not repeatedly rub or massage a sensitive area to test whether the nerve has recovered.
A small diary can make follow-up more useful. Record pain episodes, sleep and one daily task alongside treatment changes. You do not need to monitor every sensation throughout the day. A brief entry at a regular time is usually easier to maintain.
- Choose clothing that avoids rubbing the affected area.
- Plan manageable activity and short breaks around your current tolerance.
- Tell your clinician if side effects interfere with balance, concentration or daily tasks.
- Agree one practical goal, such as wearing normal clothing more comfortably or sleeping for longer.
How Long Will It Last, and Can Vaccination Help?
Symptoms often improve gradually, but recovery varies. Pain can continue for months and sometimes beyond a year. Avoid promises of a fixed cure date. Improvement may first show up as fewer night-time awakenings or better tolerance of clothing.
Shingles vaccination reduces the risk of shingles and postherpetic neuralgia. It is prevention, not a treatment for established nerve pain. Discuss eligibility and timing with your clinician, including after a previous shingles episode; local recommendations and availability matter.
When Is a Pain Specialist Review Useful?
Seek further help if pain substantially affects sleep or daily activity, or if initial medicines provide insufficient relief or troublesome side effects. A review should check the diagnosis, previous treatment and what you most want to regain.
Our guide on talking to a doctor about pain can help you prepare those details. At a Jain Pain Clinic consultation, bring the full treatment history and agree practical goals and a follow-up point. You should leave understanding what is being tried and how its benefit will be judged.
Resources
Frequently asked questions
Can shingles still hurt after the rash disappears?
Yes. The affected nerves may remain painful after the skin heals. Persistent or disruptive pain should be assessed.
Do I need to wait three months before seeking help?
No. The term postherpetic neuralgia often describes pain lasting at least three months after rash onset, but troublesome pain deserves care earlier.
Does pain after shingles mean I am still contagious?
Lingering nerve pain itself is not contagious. During an active shingles episode, contact with blister fluid can transmit the virus and cause chickenpox in susceptible people. Follow advice about covering the rash and avoiding vulnerable contacts.
Will another course of antivirals cure established nerve pain?
Antivirals treat a fresh shingles episode. They are not a routine cure for established postherpetic neuralgia; ongoing pain needs its own assessment and treatment plan.
Can the shingles vaccine treat my current pain?
No. Vaccination helps prevent future shingles and related complications. Ask your clinician about suitability and timing after recovery.